Cart

Oops, your cart is still empty
Looks like you haven’t added anything yet. Start exploring our products and find what you need.
A narrative literature review of preclinical, clinical, and approved-indication evidence
Tirzepatide, originally developed under the designation LY3298176, is a once-weekly subcutaneous peptide that acts as an agonist at both the glucose-dependent insulinotropic polypeptide (GIP) and the glucagon-like peptide-1 (GLP-1) receptors. GIP and GLP-1 are the two principal incretin hormones — gut-derived peptides released in response to nutrient intake that contribute to glucose-dependent insulin secretion. Most earlier incretin-based therapies targeted the GLP-1 receptor alone; tirzepatide was designed as a single molecule engaging both incretin pathways, and it is the first such dual GIP/GLP-1 receptor agonist to advance through large phase 3 programs and reach regulatory approval. This review summarizes the published evidence base for the compound, distinguishing throughout between preclinical findings, clinical-trial data, and approved-indication evidence so that each statement is matched to the level of evidence that supports it.
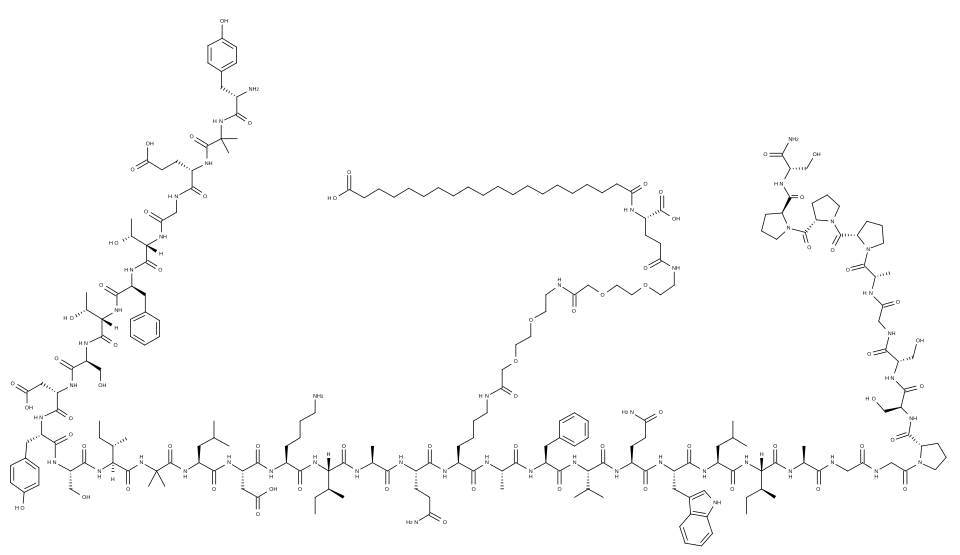
Tirzepatide is a 39-amino-acid linear peptide engineered from the native GIP sequence and conjugated to a C20 fatty diacid moiety (molecular formula C225H348N48O68; PubChem CID 156588324) [2]. As described in the discovery work by Coskun and colleagues, this acylation enables binding to serum albumin and extends the circulating half-life to approximately five days (about 117 hours), supporting once-weekly administration; non-coded amino-acid substitutions (α-aminoisobutyric acid at positions 2 and 13) are reported to confer resistance to enzymatic degradation by dipeptidyl peptidase-4 [1]. In that work the molecule bound the GIP receptor with affinity comparable to native GIP and the GLP-1 receptor with weaker affinity than native GLP-1, and in rodent models the dual mechanism produced greater glucose and weight effects than GLP- 1-receptor agonism alone [1]. These mechanistic observations derive primarily from in vitro systems, animal models, and early human pharmacology; they describe the proposed biological basis for the compound’s activity rather than confirmed therapeutic outcomes, which are addressed by the controlled trials below.
The clinical program in type 2 diabetes (the SURPASS series) has been the most extensively reported and spans monotherapy, add-on, and active-comparator designs. In SURPASS-1, a 40- week, double-blind, placebo-controlled phase 3 trial, tirzepatide was studied as monotherapy in 478 adults with type 2 diabetes inadequately controlled with diet and exercise. Across the 5-mg, 10-mg, and 15-mg doses, reductions in glycated hemoglobin (HbA1c) of approximately 1.87%, 1.89%, and 2.07% from baseline were reported, versus a small increase (+0.04%) with placebo, accompanied by dose-dependent body-weight loss of roughly 7.0 to 9.5 kg [3]. SURPASS-2 provided a direct active comparison: in this 40-week trial of 1,879 adults receiving metformin, all three tirzepatide doses lowered HbA1c more than once-weekly semaglutide 1 mg, with estimated treatment differences favoring tirzepatide that began at about −0.15 percentage points for the 5- mg dose and widened at higher doses [4]. Two further trials compared tirzepatide against basal insulin. In SURPASS-3, tirzepatide added to metformin (with or without an SGLT2 inhibitor) lowered HbA1c more than titrated insulin degludec — with estimated treatment differences of roughly −0.6 to −1.0 percentage points — and reduced body weight (about −7.5 to −12.9 kg), whereas degludec was associated with weight gain [5]. SURPASS-4, the largest and longest study in the program, evaluated tirzepatide against insulin glargine in adults with type 2 diabetes and elevated cardiovascular risk; it reported a greater HbA1c reduction (estimated difference about −0.99 percentage points) with a lower incidence of hypoglycemia at the doses studied [6]. Across these comparisons the consistent pattern was greater glycemic and weight effects relative to the active comparators, reported in the trials’ own measured terms rather than as claims of universal benefit.
Weight reduction was examined in the dedicated SURMOUNT program. SURMOUNT-1 was a 72-week, double-blind, placebo-controlled trial in 2,539 adults with obesity (or overweight with a weight-related complication) but without type 2 diabetes. Mean reductions in body weight of −15.0%, −19.5%, and −20.9% were reported for the 5-mg, 10-mg, and 15-mg doses, compared with −3.1% on placebo [7]. SURMOUNT-2 extended the question to adults who had both obesity and type 2 diabetes; over 72 weeks, mean body-weight reductions of approximately −12.8% (10 mg) and −14.7% (15 mg) were reported, versus about −3.2% with placebo, with a safety profile the authors characterized as consistent with other incretin-based therapies [8]. These figures describe averaged trial outcomes and should not be read as expected results for any individual.
Tirzepatide was also studied in obstructive sleep apnea (OSA) in the SURMOUNT-OSA trials reported by Malhotra and colleagues. These two phase 3 trials enrolled adults with moderate-to- severe OSA and obesity, with separate trials for participants who were not using positive airway pressure (PAP) therapy and those who were. Over 52 weeks, treatment reduced the apnea- hypopnea index (AHI, the standard measure of OSA severity) by an estimated 20.0 events per hour more than placebo in the non-PAP trial and 23.8 events per hour more in the PAP trial, alongside improvements in body weight, systolic blood pressure, and high-sensitivity C-reactive protein [9]. This represents clinical-trial evidence in a specific comorbid population. As with the other programs, the findings describe averaged effects under study conditions and were reported with corresponding measures of variability rather than as guarantees of individual response.
Distinguishing trial-stage evidence from approved use is central to an accurate account of tirzepatide. At the time the SURMOUNT-1 report was published, tirzepatide had already been approved by the US Food and Drug Administration for the treatment of type 2 diabetes, as the article notes [7]. Building on that approved indication, the SURMOUNT program then established the compound’s efficacy for chronic weight management in adults with obesity without diabetes (SURMOUNT-1 [7]) and with type 2 diabetes (SURMOUNT-2 [8]), and in adults with moderate-to- severe obstructive sleep apnea and obesity (SURMOUNT-OSA [9]). Keeping these apart matters: a claim should track the specific population and endpoint of the trial that supports it, rather than being generalized from the approved type 2 diabetes indication to every setting in which the compound has been studied.
Several considerations help place the published data in context. The pivotal trials were predominantly sponsored by the manufacturer and used active or placebo comparators over defined follow-up periods, typically 40 to 72 weeks; they were designed around surrogate and intermediate endpoints such as HbA1c, body weight, and the apnea-hypopnea index rather than around long-term hard outcomes, several of which continue to be evaluated in dedicated studies. Trial populations were defined by specific eligibility criteria, so the averaged effects reported may not transfer directly to every patient in routine practice. The comparative result in SURPASS-2 applies to the particular semaglutide dose studied (1 mg) and should not be generalized beyond that comparison [4]. None of these points contradicts the trial findings; rather, they clarify the boundary between what the evidence establishes and what remains under investigation, which is the appropriate posture for research-oriented writing on this compound.
Across the SURPASS and SURMOUNT trials, the most frequently reported adverse events were gastrointestinal — including nausea, diarrhea, and vomiting — and were generally described as mild to moderate and most common during dose escalation [4,7,8]. In the placebo-controlled diabetes monotherapy setting, no clinically significant or severe hypoglycemia was reported with tirzepatide [3], and the overall tolerability profile was characterized as broadly consistent with the incretin (GLP-1 receptor agonist) class [8]. As with any prescription therapy, the published trials reflect monitored study conditions and defined eligibility criteria; they do not substitute for individualized clinical judgment, and full prescribing information should be consulted for contraindications, warnings, and monitoring requirements.
The evidence for tirzepatide spans a clear hierarchy. Preclinical and discovery work established its design as a dual GIP/GLP-1 receptor agonist and proposed its mechanism [1,2]. A large, randomized phase 3 program then generated clinical data on glycemic control in type 2 diabetes [3,4,5,6] and on body weight in obesity, with and without diabetes [7,8], later extended to obstructive sleep apnea [9]. Tirzepatide is an approved therapy for type 2 diabetes [7], and this same body of trial evidence underlies its use in weight management and sleep apnea. Reading the literature in these terms — preclinical versus clinical versus approved — keeps the available evidence aligned with the claims it can actually support, which is the standard this kind of research-oriented writing is held to.
1. Coskun T, Sloop KW, Loghin C, et al. LY3298176, a novel dual GIP and GLP-1 receptor agonist for the treatment of type 2 diabetes mellitus: From discovery to clinical proof of concept. Mol Metab. 2018;18:3–14.
2. National Center for Biotechnology Information (NIH), PubChem Compound Summary for CID 156588324, Tirzepatide (C225H348N48O68). U.S. National Library of Medicine. https://pubchem.ncbi.nlm.nih.gov/compound/156588324
3. Rosenstock J, Wysham C, Frías JP, et al. Efficacy and safety of a novel dual GIP and GLP-1 receptor agonist tirzepatide in patients with type 2 diabetes (SURPASS-1): a double-blind, randomised, phase 3 trial. Lancet. 2021;398(10295):143–155. ClinicalTrials.gov NCT03954834.
4. Frías JP, Davies MJ, Rosenstock J, et al. Tirzepatide versus semaglutide once weekly in patients with type 2 diabetes (SURPASS-2). N Engl J Med. 2021;385(6):503–515. ClinicalTrials.gov NCT03987919.
5. Ludvik B, Giorgino F, Jódar E, et al. Once-weekly tirzepatide versus once-daily insulin degludec as add-on to metformin with or without SGLT2 inhibitors in patients with type 2 diabetes (SURPASS-3): a randomised, open-label, parallel-group, phase 3 trial. Lancet. 2021;398:583–598. ClinicalTrials.gov NCT03882970.
6. Del Prato S, Kahn SE, Pavo I, et al. Tirzepatide versus insulin glargine in type 2 diabetes and increased cardiovascular risk (SURPASS-4): a randomised, open-label, parallel- group, multicentre, phase 3 trial. Lancet. 2021;398(10313):1811–1824. ClinicalTrials.gov NCT03730662.
7. Jastreboff AM, Aronne LJ, Ahmad NN, et al. Tirzepatide once weekly for the treatment of obesity (SURMOUNT-1). N Engl J Med. 2022;387(3):205–216. ClinicalTrials.gov NCT04184622.
8. Garvey WT, Frias JP, Jastreboff AM, et al. Tirzepatide once weekly for the treatment of obesity in people with type 2 diabetes (SURMOUNT-2): a double-blind, randomised, multicentre, placebo-controlled, phase 3 trial. Lancet. 2023;402(10402):613–626. ClinicalTrials.gov NCT04657003.
9. Malhotra A, Grunstein RR, Fietze I, et al. Tirzepatide for the treatment of obstructive sleep apnea and obesity (SURMOUNT-OSA). N Engl J Med. 2024;391(13):1193–1205 (published correction, N Engl J Med 2024;391:1464). ClinicalTrials.gov NCT05412004.









