Cart

Oops, your cart is still empty
Looks like you haven’t added anything yet. Start exploring our products and find what you need.
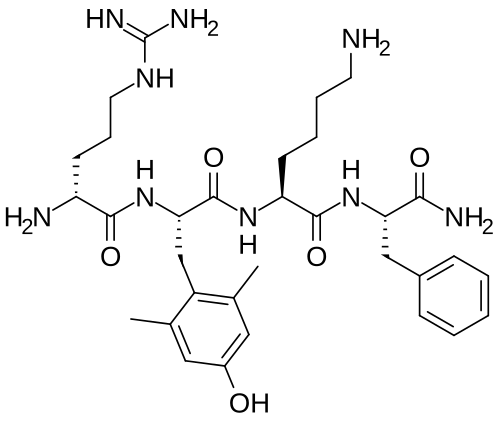
Elamipretide (FORZINITY®, SS-31, MTP-131, Bendavia) is a mitochondria-targeted synthetic tetrapeptide developed to modulate mitochondrial function under conditions of cellular stress.1 In 2025, the U.S. Food and Drug Administration (FDA) granted accelerated approval for elamipretide as the first approved treatment for Barth syndrome, a rare X-linked genetic mitochondrial disorder caused by defective cardiolipin remodeling.2,3
Elamipretide consists of four amino acids arranged as D-Arg-Dmt-Lys-Phe-NH2. Unlike ribosomally synthesized peptides composed of the 20 genetically encoded L-amino acids, elamipretide incorporates non-proteinogenic structural features, including a D-arginine residue, a synthetic tyrosine analog (2′,6′-dimethyltyrosine), and a C-terminally amidated phenylalanine. These modifications contribute to the peptide’s physicochemical properties and are believed to facilitate its interaction with mitochondrial membranes.1
Mitochondria are double-membrane organelles responsible for cellular energy production through oxidative phosphorylation. The inner mitochondrial membrane contains the electron transport chain complexes and ATP synthase, which generate ATP by establishing and utilizing a proton gradient. Efficient ATP production depends on the highly organized structure of the inner mitochondrial membrane and the coordinated function of its respiratory protein complexes. Disruption of this organization is a hallmark of mitochondrial dysfunction and contributes to numerous diseases.1
Elamipretide’s proposed mitochondrial targeting mechanism is attributed to its small size, positive charge, and amphipathic structure, meaning that it contains both hydrophobic and positively charged regions that allow it to interact with lipid membranes. These properties enable elamipretide to accumulate within the negatively charged inner mitochondrial membrane, where it associates with a phospholipid called cardiolipin.1
Cardiolipin is found primarily in the inner mitochondrial membrane, comprising 15–20% of total mitochondrial phospholipid content. It is structurally distinct from most membrane phospholipids. Typical glycerophospholipids contain a glycerol backbone attached to two esterified fatty acid chains and a phosphate-containing head group. In contrast, cardiolipin is composed of two phosphatidic acid units linked by a central glycerol bridge. Each phosphatidic acid unit contains a glycerol backbone with two esterified fatty acid chains and a phosphate group, resulting in a molecule with four fatty acid chains and two phosphate groups. This unique architecture gives cardiolipin a conical shape that influences membrane curvature and the organization of mitochondrial cristae. In addition, cardiolipin contributes to the assembly and stability of respiratory chain complexes involved in mitochondrial bioenergetic function.4
Because cardiolipin plays a central role in maintaining mitochondrial membrane organization and respiratory function, alterations in its structure, content, or fatty acyl chain composition can have profound effects on mitochondrial bioenergetics. Cardiolipin abnormalities may result from impaired biosynthesis or remodeling, as well as oxidative damage caused by reactive oxygen species (ROS). These changes disrupt interactions between cardiolipin and respiratory chain complexes, leading to impaired electron transport, reduced ATP production, and progressive mitochondrial dysfunction. These observations have prompted the development of therapeutic strategies aimed at preserving cardiolipin structure and function. One such strategy is elamipretide, a mitochondria-targeted tetrapeptide designed to interact with cardiolipin and preserve mitochondrial function under conditions of cellular stress.4
Elamipretide preferentially localizes to the inner mitochondrial membrane, where it associates with cardiolipin through electrostatic and hydrophobic interactions. Rather than acting solely through direct cardiolipin binding, these interactions are proposed to modulate the electrostatic surface potential of cardiolipin-rich membranes, thereby influencing the organization and function of cardiolipin-dependent protein complexes. This stabilization preserves mitochondrial cristae architecture and promotes the assembly and stability of respiratory chain supercomplexes, thereby supporting more efficient electron transport. In experimental models, these effects have been associated with improved electron transport efficiency, enhanced oxidative phosphorylation and ATP production, reduced mitochondrial reactive oxygen species (ROS) generation, preservation of mitochondrial membrane potential, and improved mitochondrial morphology. These effects may also help limit downstream events associated with mitochondrial dysfunction, including opening of the mitochondrial permeability transition pore (mPTP), mitochondrial swelling, and apoptosis. Collectively, these findings support the hypothesis that elamipretide preserves mitochondrial bioenergetics under conditions of cellular stress. More broadly, recent evidence suggests that mitochondrial dysfunction reflects complex interactions among membrane structure, bioenergetics, and multiple protein complexes rather than alteration of a single molecular target. Accordingly, by acting at the level of the inner mitochondrial membrane, elamipretide may influence several interconnected mitochondrial processes simultaneously.5
Preclinical studies have evaluated elamipretide in a wide range of cell culture and animal models of mitochondrial dysfunction. Across these models, treatment has generally been associated with improved mitochondrial respiration, enhanced ATP production, preservation of mitochondrial structure, and reduced oxidative stress. These mitochondrial effects have translated into functional improvements across multiple organ systems, including the cardiovascular, renal, and nervous systems.1
Cardiovascular disease represents the most extensively studied preclinical application of elamipretide. Because mitochondrial dysfunction contributes to the pathophysiology of heart failure, cardiovascular models have been widely used to evaluate its therapeutic potential. In animal models of heart failure and myocardial infarction, chronic elamipretide treatment improved left ventricular function while restoring mitochondrial bioenergetics, reducing oxidative stress, and preserving mitochondrial structure. These bioenergetic improvements were accompanied by attenuation of adverse ventricular remodeling, including reduced myocardial hypertrophy and fibrosis.6,7 In addition to its effects on the myocardium, elamipretide produced dose-dependent improvements in skeletal muscle mitochondrial function while restoring muscle morphology in animal models of heart failure, suggesting that its benefits may extend beyond cardiac tissue.8 Comparable cardioprotective effects have also been reported in experimental models of doxorubicin-induced cardiomyopathy, where elamipretide reduced myocardial apoptosis and fibrosis, findings consistent with preservation of mitochondrial function.9,10
Similar benefits have been observed in renal disease models characterized by mitochondrial dysfunction. In experimental models of ischemia-reperfusion injury and diabetic nephropathy, elamipretide maintained mitochondrial integrity and limited the downstream consequences of ischemia-reperfusion and metabolic stress. These effects were accompanied by reduced renal injury and fibrosis, suggesting that preservation of mitochondrial function may help protect against both acute and chronic kidney damage.11,12
Neurodegenerative disease models have also provided evidence supporting the neuroprotective potential of elamipretide. In experimental models of Alzheimer’s13 and Parkinson’s diseases14, treatment supported mitochondrial function while protecting vulnerable neuronal populations from degeneration. In Alzheimer’s disease models, elamipretide attenuated amyloid-β-induced mitochondrial dysfunction13, whereas in Parkinson’s disease models it preserved dopaminergic neurons.14 Collectively, these findings suggest that preservation of mitochondrial bioenergetics may help mitigate neuronal injury.15
Barth syndrome is caused by loss-of-function mutations in the X-linked TAFAZZIN gene, which encodes a phospholipid transacylase required for cardiolipin remodeling in the inner mitochondrial membrane. Defective tafazzin activity results in abnormal cardiolipin composition, impaired mitochondrial bioenergetics, and destabilization of respiratory supercomplexes. In a tafazzin knockdown mouse model of Barth syndrome, elamipretide improved mitochondrial respiratory capacity, promoted respiratory supercomplex assembly, and partially restored mitochondrial ultrastructure. These mitochondrial improvements were accompanied by improved cardiac function, providing preclinical support for the subsequent clinical development of elamipretide in Barth syndrome.16
Preclinical studies have demonstrated that elamipretide preserves mitochondrial ultrastructure and function across diverse models, including Barth syndrome, cardiomyopathy, ischemia-reperfusion injury, heart failure, aging, and diabetic retinopathy. Reported effects include improved cristae organization, mitochondrial respiration, respiratory supercomplex assembly, ATP generation, preservation of mitochondrial membrane potential, and reduced reactive oxygen species (ROS) generation.5 Taken together, these findings demonstrate generally consistent biological effects across diverse models of mitochondrial dysfunction. Although the affected organs differ, these shared improvements in mitochondrial structure and bioenergetics provided the rationale for subsequent clinical evaluation of elamipretide in several human diseases.
Despite encouraging findings in preclinical models, clinical evaluation of elamipretide has produced mixed results across a range of mitochondrial disorders. Overall, the drug has demonstrated a favorable safety profile, but improvements in clinical outcomes have varied depending on the disease being studied, trial design, and endpoint selection.
The Phase 2a EMBRACE-STEMI trial evaluated intravenous elamipretide in patients undergoing primary percutaneous coronary intervention for acute ST-elevation myocardial infarction. Although treatment was safe and well tolerated, it did not significantly reduce infarct size or improve secondary clinical or imaging outcomes.17 The PROGRESS-HF Phase 2 trial evaluated subcutaneous elamipretide in patients with stable heart failure with reduced ejection fraction (HFrEF). In this randomized, double-blind, placebo-controlled study, elamipretide was well tolerated but did not significantly improve the primary endpoint of left ventricular end-systolic volume, left ventricular ejection fraction, or other measures of cardiac function after four weeks of treatment compared with placebo.18 Thus, neither cardiovascular trial met its primary efficacy endpoint, despite demonstrating favorable safety and tolerability.
Elamipretide has also been evaluated for the treatment of dry age-related macular degeneration (AMD). Two Phase 1 open-label ReCLAIM studies demonstrated that daily subcutaneous elamipretide was generally safe and well tolerated and suggested improvements in visual function, particularly under low-luminance conditions.19,20 These encouraging findings led to the randomized, placebo-controlled Phase 2 ReCLAIM-2 trial in patients with dry AMD and noncentral geographic atrophy. Although the study did not meet its primary endpoints of low-luminance visual acuity and geographic atrophy progression, elamipretide was associated with preservation of the ellipsoid zone, a marker of photoreceptor integrity, and a greater proportion of patients experienced clinically meaningful improvements in low-luminance visual acuity compared with placebo.21 These findings supported continued clinical development despite failure to achieve the primary efficacy endpoints.
The Phase 3 MMPOWER-3 trial evaluated subcutaneous elamipretide in 218 patients with genetically confirmed primary mitochondrial myopathy. Although elamipretide was generally well tolerated, it did not significantly improve the coprimary endpoints of six-minute walk distance or patient-reported fatigue after 24 weeks of treatment compared with placebo. Exploratory subgroup analyses suggested a possible benefit in patients with nuclear DNA-associated disease, but these findings require confirmation in future studies.22
The strongest clinical evidence supporting elamipretide has been obtained in Barth syndrome (BTHS), a rare X-linked mitochondrial disorder resulting from abnormal cardiolipin metabolism. BTHS affects approximately one in one million male births and is characterized by multisystem involvement, including left ventricular noncompaction and cardiomyopathy, skeletal myopathy, intermittent neutropenia, growth delay, and exercise intolerance. The TAZPOWER program evaluated elamipretide in patients with Barth syndrome. Although the initial randomized, placebo-controlled phase did not meet its primary efficacy endpoints after 12 weeks of treatment, the subsequent 168-week open-label extension demonstrated sustained improvements in exercise capacity, muscle strength, fatigue, and cardiac function, while maintaining a favorable safety profile. Long-term treatment was also associated with improvements in the monolysocardiolipin-to-cardiolipin (MLCL/CL) ratio, a biochemical marker of Barth syndrome.23 These findings supported the FDA’s accelerated approval of elamipretide as the first approved treatment for Barth syndrome in 2025 under the formulation name FORZINITY®.2,3
Because elamipretide has been investigated for its effects on mitochondrial bioenergetics, muscle function, and exercise capacity, its status under anti-doping regulations is relevant to some athletes. Following FDA approval in 2025, elamipretide is no longer classified as a non-approved substance (S0) under the World Anti-Doping Agency (WADA) Prohibited List. However, the WADA Prohibited List does not identify elamipretide under another prohibited category. Accordingly, athletes subject to anti-doping regulations should verify its current status through WADA, USADA, GlobalDRO, or their sport’s anti-doping organization before use.24
Elamipretide is among the most extensively studied mitochondria-targeted therapeutics. Preclinical studies demonstrate preservation of mitochondrial structure and bioenergetic function across multiple disease models, whereas clinical trials have produced more variable results. Despite these mixed outcomes, the FDA approval of elamipretide for Barth syndrome represents an important milestone in the development of mitochondria-targeted therapies. Ongoing clinical studies will further define its therapeutic role in other diseases associated with mitochondrial dysfunction. Collectively, the available evidence suggests that preserving inner mitochondrial membrane integrity may represent a promising therapeutic strategy for diseases characterized by mitochondrial dysfunction.
FDA Grants Accelerated Approval to First Treatment for Barth Syndrome
FDA FORZINITY (Elamipretide) Prescribing Information
Elamipretide: A Review of Its Structure, Mechanism of Action, and Therapeutic Potential
Contemporary insights into elamipretide’s mitochondrial mechanism of action and therapeutic effects
1. Tung C, Varzideh F, Farroni E, Mone P, Kansakar U, Jankauskas SS, et al. Elamipretide: A review of its structure, mechanism of action, and therapeutic potential. Int J Mol Sci. 2025;26(3):944. doi:10.3390/ijms26030944.
2. U.S. Food and Drug Administration. FDA grants accelerated approval to first treatment for Barth syndrome [Internet]. Silver Spring (MD): U.S. Food and Drug Administration; 2025 Sep 19 [cited 2026 Jul 8]. Available from: https://www.fda.gov/news-events/press-announcements/fda-grants-accelerated-approv al-first-treatment-barth-syndrome
3. U.S. Food and Drug Administration. FORZINITY (elamipretide) injection, for subcutaneous use: prescribing information [Internet]. Silver Spring (MD): U.S. Food and Drug Administration; 2025 Sep [cited 2026 Jul 8]. Available from: https://www.accessdata.fda.gov/drugsatfda_docs/label/2025/215244s000lbl.pdf
4. Paradies G, Paradies V, Ruggiero FM, Petrosillo G. Role of cardiolipin in mitochondrial function and dynamics in health and disease: molecular and pharmacological aspects. Cells. 2019;8(7):728. doi:10.3390/cells8070728.
5. Sabbah HN, Alder NN, Sparagna GC, Bruce JE, Stauffer BL, Chao LH, et al. Contemporary insights into elamipretide’s mitochondrial mechanism of action and therapeutic effects. Biomed Pharmacother. 2025 Jun;187:118056. doi:10.1016/j.biopha.2025.118056.
6. Sabbah HN, Gupta RC, Kohli S, Wang M, Hachem S, Zhang K. Chronic therapy with elamipretide (MTP-131), a novel mitochondria-targeting peptide, improves left ventricular and mitochondrial function in dogs with advanced heart failure. Circ Heart Fail. 2016;9(2):e002206. doi:10.1161/CIRCHEARTFAILURE.115.002206.
7. Shi J, Dai W, Hale SL, Brown DA, Wang M, Han X, et al. Bendavia restores mitochondrial energy metabolism gene expression and suppresses cardiac fibrosis in the border zone of the infarcted heart. Life Sci. 2015;141:170-178. doi:10.1016/j.lfs.2015.09.022.
8. Sabbah HN, Gupta RC, Singh-Gupta V, Zhang K. Effects of elamipretide on skeletal muscle in dogs with experimentally induced heart failure. ESC Heart Fail. 2019;6(2):328-335. doi:10.1002/ehf2.12408.
9. Yeh JN, Sung PH, Chiang JY, Sheu JJ, Huang CR, Chu YC, et al. Early treatment with combination of SS31 and Entresto effectively preserved the heart function in doxorubicin-induced dilated cardiomyopathic rat. Biomed Pharmacother. 2021;141:111886. doi:10.1016/j.biopha.2021.111886.
10. Zhang L, Feng M, Wang X, Zhang H, Ding J, Cheng Z, et al. Peptide Szeto-Schiller 31 ameliorates doxorubicin-induced cardiotoxicity by inhibiting the activation of the p38 MAPK signaling pathway. Int J Mol Med. 2021;47(4):63. doi:10.3892/ijmm.2021.4896.
11. Szeto HH, Liu S, Soong Y, Alam N, Prusky GT, Seshan SV. Protection of mitochondria prevents high-fat diet-induced glomerulopathy and proximal tubular injury. Kidney Int. 2016;90(5):997-1011. doi:10.1016/j.kint.2016.06.013.
12. Ding XW, Robinson M, Li R, Aldhowayan H, Geetha T, Ramesh Babu J. Mitochondrial dysfunction and beneficial effects of mitochondria-targeted small peptide SS-31 in diabetes mellitus and Alzheimer’s disease. Pharmacol Res. 2021;171:105783. doi:10.1016/j.phrs.2021.105783.
13. Manczak M, Mao P, Calkins MJ, Cornea A, Reddy AP, Murphy MP, et al. Mitochondria-targeted antioxidants protect against amyloid-beta toxicity in Alzheimer’s disease neurons. J Alzheimers Dis. 2010;20 Suppl 2:S609-S631. doi:10.3233/JAD-2010-100564.
14. Yang L, Zhao K, Calingasan NY, Luo G, Szeto HH, Beal MF. Mitochondria-targeted peptides protect against 1-methyl-4-phenyl-1,2,3,6-tetrahydropyridine neurotoxicity. Antioxid Redox Signal. 2009;11(9):2095-2104. doi:10.1089/ars.2009.2445.
15. Nhu NT, Xiao SY, Liu Y, Kumar VB, Cui ZY, Lee SD. Neuroprotective effects of a small mitochondrially-targeted tetrapeptide elamipretide in neurodegeneration. Front Integr Neurosci. 2021;15:747901. doi:10.3389/fnint.2021.747901.
16. Russo S, De Rasmo D, Signorile A, Corcelli A, Lobasso S. Beneficial effects of SS-31 peptide on cardiac mitochondrial dysfunction in tafazzin knockdown mice. Sci Rep. 2022;12(1):19847. doi:10.1038/s41598-022-24231-4.
17. Gibson CM, Giugliano RP, Kloner RA, Bode C, Tendera M, Jánosi A, et al. EMBRACE STEMI study: a Phase 2a trial to evaluate the safety, tolerability, and efficacy of intravenous MTP-131 on reperfusion injury in patients undergoing primary percutaneous coronary intervention. Eur Heart J. 2016;37(16):1296-303. doi:10.1093/eurheartj/ehv597.
18. Butler J, Khan MS, Anker SD, Fonarow GC, Kim RJ, Nodari S, et al. Effects of elamipretide on left ventricular function in patients with heart failure with reduced ejection fraction: the PROGRESS-HF Phase 2 trial. J Card Fail. 2020;26(5):429-437. doi:10.1016/j.cardfail.2020.02.001.
19. Mettu PS, Allingham MJ, Cousins SW. Phase 1 clinical trial of elamipretide in dry age-related macular degeneration and noncentral geographic atrophy: ReCLAIM NCGA study. Ophthalmol Sci. 2022;2(1):100086. doi:10.1016/j.xops.2021.100086.
20. Allingham MJ, Mettu PS, Cousins SW. Phase 1 clinical trial of elamipretide in intermediate age-related macular degeneration and high-risk drusen: ReCLAIM High-Risk Drusen study. Ophthalmol Sci. 2022;2(1):100095. doi:10.1016/j.xops.2021.100095.
21. Ehlers JP, Hu A, Boyer D, Cousins SW, Waheed NK, Rosenfeld PJ, et al. ReCLAIM-2: A randomized Phase II clinical trial evaluating elamipretide in age-related macular degeneration, geographic atrophy growth, visual function, and ellipsoid zone preservation. Ophthalmol Sci. 2025;5(1):100628. doi:10.1016/j.xops.2024.100628.
22. Karaa A, Bertini E, Carelli V, Cohen BH, Enns GM, Falk MJ, et al. Efficacy and safety of elamipretide in individuals with primary mitochondrial myopathy: the MMPOWER-3 randomized clinical trial. Neurology. 2023;101(3):e238-e252. doi:10.1212/WNL.0000000000207402.
23. Thompson WR, Manuel R, Abbruscato A, Carr J, Campbell J, Hornby B, et al. Long-term efficacy and safety of elamipretide in patients with Barth syndrome: 168-week open-label extension results of TAZPOWER. Genet Med. 2024;26(7):101138. doi:10.1016/j.gim.2024.101138.
24. World Anti-Doping Agency. Prohibited List [Internet]. Montreal (QC): World Anti-Doping Agency; 2026 [cited 2026 Jul 14]. Available from: https://www.wada-ama.org/en/resources/world-anti-doping-program/prohibited-list